
Drink water. Gain “body fat”? In one experiment, that is what the scanner reported. The fat was a calculation, not a biological event.
Researchers measured 39 adults before and after they drank two litres of water. On the multi-frequency bioimpedance system, the estimated body-fat percentage rose. The volunteers had not suddenly accumulated fat. The machine had converted a change in the body into an apparent change in its composition. The experiment was published in 2023.
The same uncertainty hides inside a much more ordinary result: your InBody report says 18.4% body fat today and 16.8% a month later. Did you lose fat, or did the measurement model change its mind? A precise-looking decimal is not a promise of biological accuracy.
The electrical signal may be measured consistently. Fat, muscle and even the calorie estimate are inferred through equations. Understanding that gap tells us when bioelectrical impedance analysis (BIA) is useful, and when a convincing-looking change deserves scepticism.
Original article: Mikhail Faranov, MD (2023). Substantial revision, new research, calculations and scientific editing: Ilya Nikitin, PhD (22 October 2026). This update is an editorial evidence review, not an independently peer-reviewed clinical study.
Change in estimated body-fat percentage after drinking water, using multi-frequency BIA
Source: Jeong et al., 2023 (39-person experiment). These are reported group mean changes, not individual outcomes. Bars use a 0–3 percentage-point scale. The study used a 2-litre challenge, not a normal glass of water; the effect must not be generalised to every device.
Key Takeaways
- Measured signal, estimated tissue. BIA measures electrical impedance; body fat, muscle mass and metabolic rate are model-derived outputs, not direct measurements.
- Accuracy is not the same as tracking. A device may misestimate your actual body-fat percentage yet still help you spot changes over time. How useful it is depends on the model and repeatability.
- Consistency matters. The same machine, similar conditions and changes sustained across several visits are more informative than comparing isolated readings from different devices.
- Water can produce counterintuitive results. One experiment found that drinking 2 litres of water increased, rather than decreased, the estimated fat percentage on the BIA systems tested.
What an InBody machine actually measures
A BIA machine sends a tiny electrical current through the body and records how tissues oppose it. That signal, called impedance, includes resistance (R) and reactance (Xc).
Water-rich tissues conduct electricity differently from fat. Different machines measure different body regions and frequencies, so estimates can vary between devices.
The machine does not see fat cells or muscle fibres directly. Its software combines the electrical signal with information such as weight, height, age and sex to estimate body composition. The equations can differ between brands. [1, 2]
Many conventional BIA models treat fat-free mass as roughly 73% water. If estimated body water is 40 litres, the calculation produces about 54.8 kg of fat-free mass; estimated fat is what remains after subtracting that from body weight. This illustrates a model, not a disclosed InBody formula. [1, 3]
Our calculation: change the assumption, change the “fat”
Mike’s Balance checked how sensitive a simplified body-fat calculation is to one assumption. Hold body weight fixed at 80 kg and the model’s estimated total body water at 40 litres. Now vary only the assumed water fraction of fat-free mass, from 71% to 75%. The body and the electrical reading have not changed; only our interpretation has.
| Assumed water in fat-free mass | Estimated fat-free mass | Estimated body fat |
|---|---|---|
| 71% (illustrative) | 56.34 kg | 29.6% |
| 73% (conventional) | 54.79 kg | 31.5% |
| 75% (illustrative) | 53.33 kg | 33.3% |
Difference between the two illustrative extremes: 3.8 percentage points.
Reproduce it: estimated fat-free mass = 40 ÷ hydration fraction; estimated fat % = 100 × [1 − estimated fat-free mass ÷ 80]. The values are rounded only at display.
Important: This is our arithmetic sensitivity analysis, not a measurement experiment, a confidence interval, a clinically established range of hydration fractions, or a disclosed InBody algorithm. The 71% and 75% scenarios are chosen to expose the model’s sensitivity, not to describe the distribution in healthy adults.
The NHANES 2003–2004 documentation describes a research instrument that measured resistance and reactance at 50 frequencies, then used equations to estimate body water, fat-free mass and fat percentage. One modelling assumption was 73.2% water in fat-free mass. Each step adds uncertainty, and none of this means InBody uses the same formula.
The electrical signal can be precise while the final body-fat estimate is not. Extra decimal places cannot remove uncertainty from the model.
How accurate are body-fat scales? Three questions, not one
People often ask whether a BIA machine is accurate when they really mean three different things. Repeatability asks whether it produces similar numbers when nothing meaningful changes. Bias asks whether it is systematically higher or lower than a reference method. Individual agreement asks how far the estimate for one person might fall from that reference.
These properties can coexist: a scale may consistently report your body-fat percentage several points too low, yet still follow a genuine change. But good repeatability alone does not prove that it will correctly measure fat loss over time.
Our NHANES reanalysis: why two methods disagree
We wanted to see what this distinction looks like beyond a small laboratory study. Mike’s Balance reanalysed publicly available measurements from NHANES 2003–2004, matching bioimpedance and DXA results for the same people. Our primary analysis included 1,924 adults aged 18–49 with usable impedance data and consistent, non-imputed DXA readings. The device was a Xitron Hydra Model 4200, not an InBody machine or a modern bathroom scale.
| Mean absolute difference | 4.26 percentage points |
|---|---|
| More than 10 points apart | 6.9% of participants |
| Approximate 95% limits of agreement | −11.64 to +8.97 points |
Original descriptive analysis by Ilya Nikitin for Mike’s Balance, 22 October 2026. Unweighted, selected NHANES 2003–2004 sample (n = 1,924). “Percentage points” means the difference between two body-fat percentage readings, not the proportionate error. The limits of agreement describe variation between these two methods; they are not a universal accuracy guarantee for any device.
Here is the distinction: 33.6% of participants had body-fat readings more than five percentage points apart, but this does not mean that one in three people would get a misleading fat-loss trend. On average, the impedance estimate was only 1.33 points lower. But averaging positive and negative differences can hide how far apart the two methods are for individual people. DXA itself is an imperfect reference, so this is disagreement between methods, not a definitive measurement of which machine was wrong.
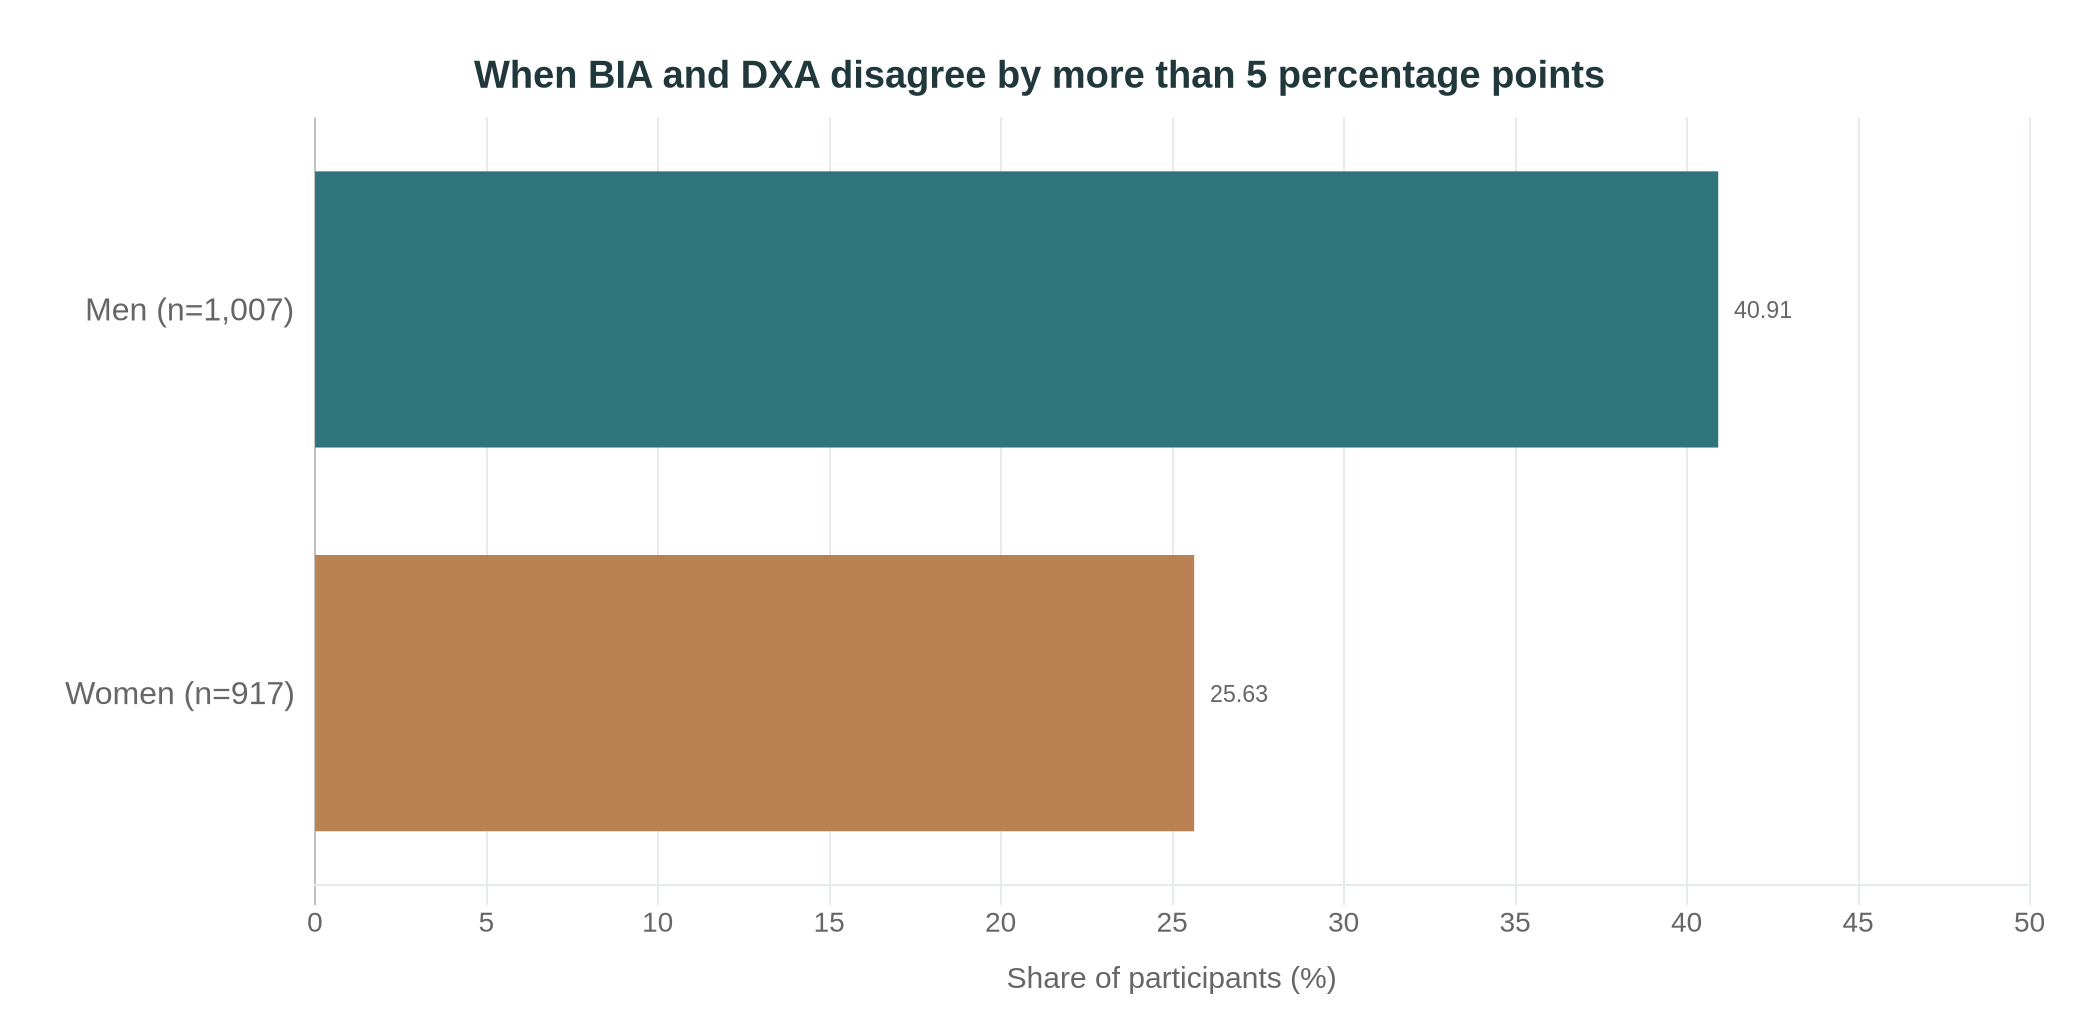
Figure: Share of participants with BIA and DXA body-fat readings more than five percentage points apart. Men: 1,007; women: 917. These were Xitron Hydra measurements, not InBody results.
The disagreement differed by sex in this selected sample. Among men, the impedance estimate averaged 2.87 points lower than DXA; among women, it averaged 0.35 points higher. A difference exceeding five points occurred in 40.9% of men and 25.6% of women. After removing the average difference separately for men and women, the share exceeding five points in the full sample fell from 33.6% to 30.5%. That remains a comparison between different people and methods, not a measure of error when following one person’s progress. These are descriptive comparisons: body composition, BMI and selection into the analysed sample also differ between groups, so the figures do not establish that one sex’s measurements are intrinsically more accurate.
How we checked it. We joined four public CDC datasets, restricted the main sample to adults aged 18–49 with usable BIA readings, and required DXA results to be consistent across all five released records. Of 1,957 initially eligible pairs, 33 failed that additional check. As a sensitivity analysis, we also analysed the five imputed DXA datasets separately and combined their survey-weighted estimates using Rubin’s rules: mean difference −1.43 points (approximate 95% confidence interval −2.02 to −0.84). This does not correct missing BIA data.
What it cannot tell us. The Xitron and DXA measurements date from 2003–2004, not the age of today’s InBody or smart scales. A one-time comparison cannot test whether a device accurately tracks fat loss. Previous researchers have also studied Xitron and DXA in NHANES; ours is a transparent reanalysis of individual differences, not a claim of being first. The analysis code and checksums are retained in a private reproducibility package; publication will be decided separately.
A 2026 review: small average bias can conceal large individual error
A 2026 systematic review compared BIA with four-compartment (4C) models in 12 studies of healthy, weight-stable adults. Mean bias in estimated body-fat percentage ranged across studies from −3.5 to +4.4 percentage points. More revealing were the 95% limits of agreement: their total span was commonly 15–20 percentage points. [4]
This does not mean that each reader’s device is wrong by 15–20 points, nor that a particular person’s expected error is half that range. These are study-dependent distributions of differences between methods, not universal confidence intervals for a brand. They do show why apparently respectable agreement between group averages may be insufficient for an individual decision.
Because the devices and study populations differed, the authors did not report a single pooled error estimate.
InBody 770: repeatable, but not the same as DXA
A controlled study of only 14 healthy adults using the InBody 770 reported very high test–retest reliability for whole-body measurements. Across visits, major whole-body estimates changed relatively little when conditions were controlled. Yet against dual-energy X-ray absorptiometry (DXA), the same system underestimated percentage body fat by a mean of about 4.0 percentage points and overestimated fat-free mass by about 2.8 kg. [5]
Do not automatically add four points to your own result. The important distinction is that an estimate can be consistently offset yet still reveal a trend.
A larger study of 1,000 healthy, physically active adults reached a useful complementary conclusion. The InBody 770 tended to report body-fat percentages lower than DXA by an average of 4.2 points in men and 2.8 in women, yet repeat measurements of the device were highly consistent. That is a reminder to distinguish a persistent offset from a noisy measurement. The latter makes changes harder to detect; an offset that remains stable may matter less for following your own trend. But a single cross-sectional comparison cannot establish the accuracy of measured fat loss.
| Evidence | Reported result | What it means |
|---|---|---|
| 2026 review: BIA vs 4C | Mean body-fat bias: −3.5 to +4.4 percentage points across studies; agreement intervals often 15–20 points wide | Individual agreement may be poor despite modest average bias. [4] |
| InBody 770 vs DXA | Mean body-fat bias: about −4.0 points; fat-free-mass bias: +2.8 kg | In this study, BIA tended to report less fat and more fat-free mass. [5] |
| InBody 230, 720 and 770: repeated tests | Minimum detectable differences for body fat: 2.12–2.73 percentage points under the study protocol | Change thresholds depend on the device, study and testing conditions. [6] |
| 2025 cross-technology study: 288 adults | Different electrical readings could yield similar fat-free-mass estimates after model-specific calibration | The equation matters alongside the hardware. [7] |
The equations matter as much as the electrodes. In a 2025 Clinical Nutrition study of 288 adults, different impedance approaches produced different raw electrical values. After equations were developed for the relevant population and reference method, their fat-free-mass estimates showed good agreement. Fat-mass estimates were less dependable at the individual level. The answer was partly in the mathematics, not only the electrodes. One co-author was affiliated with Technogym, a maker of body-composition equipment; that relevant commercial connection is disclosed in the paper and should be considered when interpreting device comparisons. [7]
Why drinking water can make a scanner report more fat
You might expect extra water to make the body look leaner to an electrical scanner. In this experiment, the opposite happened. The key is that the scale measures weight, while its estimate of the water-containing, fat-free tissues comes from a different calculation.
In a 2023 experiment involving 39 participants, researchers measured body composition before and after the participants drank 2 litres of water. On the multi-frequency BIA system, estimated body-fat percentage rose by about 2.1 percentage points in men and 2.6 points in women. Estimated fat mass increased by around 2 kg, although participants had not suddenly acquired 2 kg of adipose tissue. [8]
Another experiment found that acute water intake and the time spent standing could materially alter estimates made by a modern standing multi-frequency analyser; in the water condition, a reported rise of approximately 1.3 kg in estimated fat mass was not a real fat gain. [9]
Here is the arithmetic behind the illusion. In the experiment, the multi-frequency scanner’s estimate of total body water did not rise in men and actually fell in women. If a person weighs 80 kg with an estimated 18% body fat, drinking 2 kg of water without a corresponding rise in estimated fat-free mass would change the reported figure to roughly 20%, even though their actual fat had not changed. That illustrative two-point jump is close to the average 2.1-point increase seen in the men; it is not a calculation for a particular volunteer. Water still in the digestive tract may be poorly represented by the electrical measurement, but the experiment does not establish a single exact pathway for every device.
DXA told a different story: after drinking, it attributed about 1.4–1.7 kg more to fat-free mass on average. That is not sudden muscle growth either. Both techniques reacted to water, but they assigned it to different compartments. [Jeong et al., 2023]
Do not dehydrate yourself before testing. Measure in your normal hydration state, under similar conditions each time.
Can BIA reliably tell you whether you are losing fat?
Consider two different questions. First: is your percentage of body fat exactly 18.4%? Second: has your body composition changed over several months? The second can be easier to answer if the same device has stable systematic bias and good repeatability.
A study comparing InBody 230, 720 and 770 measured minimum detectable differences of approximately 2.12–2.73 percentage points for percentage body fat under its testing conditions. Its authors also reported relatively small individual errors versus DXA for these models, while warning about systematic and proportional biases. Smaller changes can be difficult to distinguish from measurement variability in that protocol. But this is not a universal ±2.5-point rule for every machine, age group or measurement schedule. [6]
If your scale changes from 18.4% to 16.8%, that might be progress or ordinary measurement variation. Look for a repeated trend alongside your weight and waist measurement.
But laboratory repeatability can suffer in real life, where meals, exercise and changing body water make otherwise identical tests less comparable.
What about smart scales at home?
Home scales with foot electrodes do not measure fat directly either. The electrical path mainly runs through the lower body; the scale uses an equation to estimate composition for the rest. More electrodes and frequencies can provide additional information, but neither an expensive professional scanner nor a cheap bathroom scale is automatically the best choice for everyone.
A study of 15 bioimpedance devices, including 14 consumer-grade models, compared their readings with a four-compartment laboratory model. Thirty-seven participants returned after 12–16 weeks. Some models were useful for following changes, including selected foot-to-foot scales; others performed less well. Across devices, the study’s standard error when estimating changes in body-fat percentage ranged from 1.7 to 2.6 percentage points. That is not a universal cut-off for detecting fat loss, but it explains why a small two-visit difference deserves caution. The best home scale is one you can use consistently, with a track record of validation for people resembling you.
A quick reality check for a changing printout
Before interpreting a change, ask three questions: Was it the same device and software? If not, start a new baseline. Were time of day, recent meals, exercise and fluid status broadly comparable? If not, repeat under matched conditions. Does the change persist and agree with independent measures? If not, treat it as provisional rather than as proof of fat loss or muscle gain.
Numbers from different devices and experiments are not interchangeable thresholds. A single change, however impressive, is worth checking under comparable conditions.
A practical protocol for tracking progress
- Use the same machine and software whenever possible. InBody 570, InBody 770, Tanita and household foot-only scales should not be assumed interchangeable.
- Choose a consistent time and context. Many people find a morning visit before breakfast convenient. Follow the specific manufacturer’s protocol, keeping the interval since meals, drinks and exercise similar each time.
- Avoid unusual conditions. Do not deliberately drink excessive water, restrict fluids, train hard immediately beforehand or compare measurements taken during illness, pronounced swelling or abrupt dietary changes.
- Record context. Date, time, model, weight, recent training, large meals and changes in hydration help explain anomalous results. If available, retain raw resistance and reactance values as well.
- Prefer sustained trends to single-step changes. Several consistent measurements over weeks or months are more informative than a dramatic number from one afternoon.
- Cross-check with independent indicators. Waist measurement, body weight, strength trends and, where clinically appropriate, a validated reference assessment can help distinguish tissue change from fluid shifts.
If you are evaluating a medical condition, a change in tissue water, or nutritional status during treatment, interpretation should be guided by the relevant clinical team. The protocol and thresholds used for healthy fitness tracking should not be transplanted into dialysis, severe oedema or other fluid-altering conditions.
Is DXA the final truth? Not quite
DXA uses low-dose X-rays to estimate bone mineral, fat and lean soft tissue. It is widely used as a reference method, and it avoids some of BIA’s electrical assumptions. Yet it has its own calibration, hydration and measurement errors; DXA-derived lean soft tissue should not be mistaken for a direct count of muscle fibres. [1, 4]
A four-compartment model combines more than one type of measurement, typically information about body density, water and mineral alongside body weight. By separating more of the body’s components, it reduces reliance on any single fixed relationship. It is a stronger research benchmark in many contexts, not an error-free window into tissue composition.
These distinctions matter if you want to compare numbers from two labs. Disagreement does not automatically reveal which machine is wrong. It first tells you that you have two methods making different assumptions.
The other numbers on your InBody printout
Muscle mass is an estimate, not a direct muscle measurement
Fat-free mass includes water, organs, bone, blood and other non-fat tissues. Skeletal muscle mass is a narrower quantity. If a report gives both, it has not independently weighed your muscles: it has estimated composition from electrical and anthropometric inputs. Changes in fluid status can make an apparent muscle gain especially misleading.
Basal metabolic rate is calculated
A BIA device does not directly measure how much energy your body burns at rest. Its basal metabolic rate (BMR) output is an estimate obtained from a formula or from estimated fat-free mass. Measuring resting energy expenditure requires a different method, typically indirect calorimetry. An apparent change in the BMR estimate may simply follow a change in predicted lean mass.
The InBody Score is proprietary
The InBody Score is a composite produced by the manufacturer’s own rules. It may help some users organise their results, but it is not an independently standardised clinical measure of health, fitness or longevity. An apparent score improvement needs interpretation through the underlying variables.
Phase angle: a genuine signal, not a cellular-health grade
Phase angle is derived from reactance relative to resistance, conventionally using the arctangent of Xc/R at a specified frequency. Unlike estimated fat percentage, it is closer to the original electrical measurement. That makes it scientifically interesting.
However, its value varies with age, sex, measurement geometry, device, frequency, tissue composition and disease state. Lower phase angles have been associated with poorer outcomes in some clinical populations, but no universal threshold turns one person’s score into a diagnosis of weak cells or poor health. [1]
An informal comparison: InBody 570 versus 770
The original article described repeated measurements on two models made by the same company: the InBody 570 and InBody 770. According to that account, the 570 generally produced a higher proprietary InBody Score, a higher estimate of muscle mass and a lower estimate of body-fat percentage.
These were informal observations, without paired raw measurements or control of test conditions. A 3–5% change in the proprietary score does not mean a 3–5-point change in body fat.
Different algorithms or testing conditions could explain the discrepancy.
To test whether those differences come from the machines themselves, we would need repeated measurements under matched conditions and a reference method.
The practical rule: do not combine readings from different models into one progress chart.
Should you pay for a professional BIA test?
A professional multi-frequency, multi-electrode scanner can offer segmental outputs and more consistent test conditions than a simple home scale. Yet a study in 67 healthy adults found that the more elaborate InBody 720 and 770 added little advantage over the portable InBody 230 for the tested body-composition estimates; that finding does not prove every inexpensive scale performs equally well. Price and hardware alone do not establish better performance for every person. [6, 7]
For someone checking broad changes over many months, a convenient device used consistently may be more valuable than occasional access to an elaborate machine. For an athlete trying to verify a very small fat loss, or a patient whose treatment depends on precise body-composition estimates, the threshold for evidence should be higher.
And there is no reason to manipulate water intake to obtain a flattering reading. A number engineered to look better tells you less about the body, not more.
The verdict: trust the trend carefully, not the decimal
BIA is neither a fraud nor a direct measurement of body fat. It is a genuine physical measurement followed by a model. Under controlled conditions some devices repeat remarkably well; under other conditions, differences between devices and reference methods can be substantial.
So keep the printout, but keep the context with it. If your waist, weight, training performance and repeated readings move together over time, the result becomes more credible. If your estimated muscle mass rises after a large drink of water, the instrument has not witnessed muscle growth.
The most honest use of a bioimpedance analyser is to treat its output as a useful, imperfect estimate and to ask what kind of change could have produced it.
Sources and methods
This article separates the electrical signal from the estimated result, and explains why disagreement between devices is not the same as inaccurate tracking. These results apply to particular devices and study groups, not everyone.
- Methodological guidance: Methodological standards for body composition assessment. American Journal of Clinical Nutrition, 2026; and Metrology in Bioelectrical Impedance Analysis, 2026.
- Device differences: Variations in bioelectrical impedance devices impact raw measures comparisons and subsequent prediction, 2024.
- Physiological assumptions: Relevance of hydration state of the fat free mass in estimating fat mass by body impedance analysis, 1998.
- Four-compartment comparison: The Validity of Bioelectrical Impedance Analysis Compared to a Four-Compartment Model in Healthy Adults: A Systematic Review, 2026.
- InBody 770: Reliability, biological variability, and accuracy of multi-frequency bioelectrical impedance analysis, published online 2024.
- Minimum detectable differences: Reliability and Agreement of Various InBody Body Composition Analyzers as Compared to DXA, Journal of Clinical Densitometry, 2020 (published online 2018).
- Equations across devices: Determining body composition using different bioimpedance technologies: Is an agreement possible? Clinical Nutrition, 2025.
- Two-litre hydration experiment: The effect of acute hydration on body composition assessed by multi-frequency and single-frequency bioelectrical impedance, 2023.
- Water and standing: Influence of Acute Water Ingestion and Prolonged Standing on Raw Bioimpedance and Subsequent Body Fluid and Composition Estimates, 2022.

Based on my observations, the accuracy of our InBody assessments seems to become slightly dubious as you become more physically fit. Truth be told, unless you take the scan in a fasted state with minimal water intake first thing in the morning, the results can be doubtful. Indulging in a hefty drink or meal right before stepping onto the machine can assuredly distort the readings. I once humorously “shed” 3% body fat merely by executing the scan immediately after a workout!