
Why I am keeping this case study: Liz Parrish’s experiment is exactly the kind of high-risk, high-uncertainty longevity story that can generate useful questions. It should not be treated as proof that gene therapy rejuvenates humans, but it is still worth following as an N=1 hypothesis generator.
The original hypothesis
Because the Liz Parrish story spans several claims and time points, the timeline below separates the main reported milestones from the evidence question.
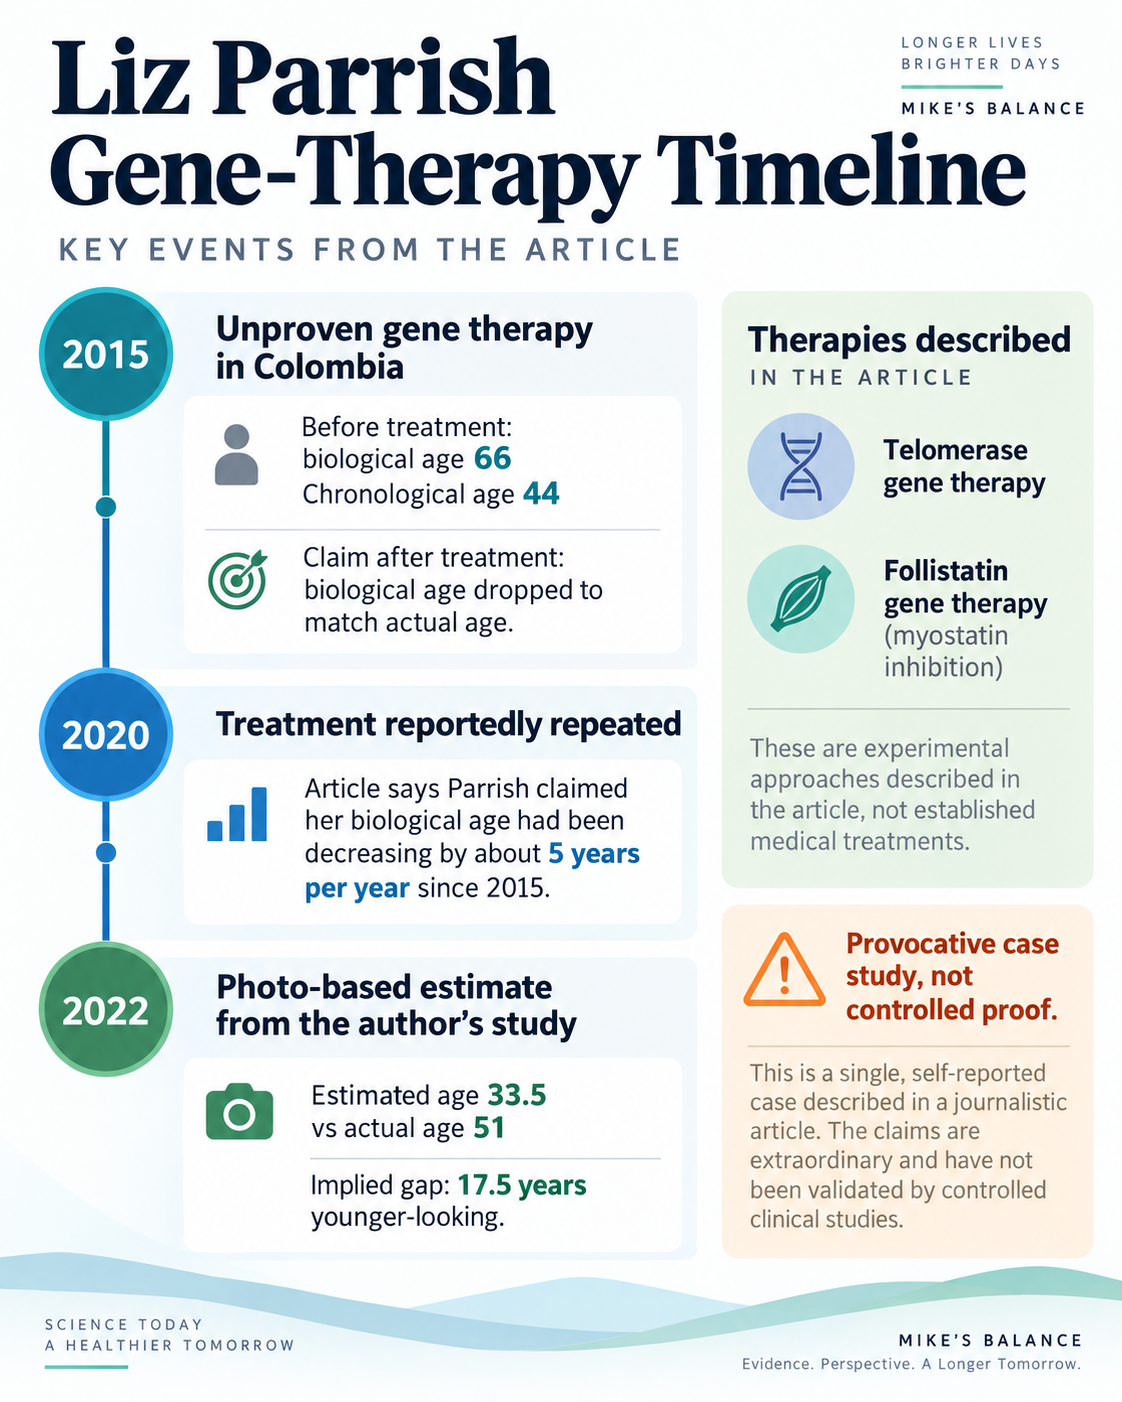
The timeline is a map of claims and observations, not a demonstration that the therapy caused rejuvenation.
My original interest was simple: if aging is partly driven by modifiable molecular pathways, could gene therapy alter some of those pathways strongly enough to change measurable aging phenotypes in a living adult? Parrish’s self-experiment made that abstract question unusually concrete.
What Liz Parrish has reported
Parrish, founder and CEO of BioViva, has publicly described receiving experimental gene therapies intended to influence aging-related biology, including telomerase-related and muscle-regulation pathways. She has also reported changes in biomarkers and physical condition after treatment.
These reports are interesting, but they are not equivalent to a randomized clinical trial. There was no blinded control group, no randomization, and the subject is also closely connected to the company promoting the intervention. That does not make the observations worthless; it means they cannot establish causality.
A correction about my “17.5 years younger” estimate
In the earlier version I wrote that my photo-based analysis suggested a biological age around 33.5 when Parrish was approximately 51, implying about 17.5 years of rejuvenation. That wording was too strong.
The correct description is: a facial age-estimation algorithm produced a younger-looking age estimate from selected photographs. That is not the same as measuring whole-body biological age, lifespan extension, organ rejuvenation or disease risk. Even sophisticated epigenetic clocks measure different constructs and currently have important limitations at the individual level.
Why the gene-therapy idea is biologically plausible
Modern geroscience does identify pathways that are potentially addressable by gene therapy. Recent reviews discuss targets such as TERT/telomerase, Klotho, sirtuins, FOXO pathways, senescence-related mechanisms and partial reprogramming. Preclinical models make the field genuinely interesting.
That is the strongest reason not to dismiss Parrish’s experiment out of hand: the broad concept is scientifically plausible and active research is moving toward it.
Why plausible is not the same as proven
- Preclinical success may not translate to humans. Lifespan and tissue effects in mice do not establish safety or efficacy in healthy adults.
- Telomerase is complicated. Telomere maintenance can be beneficial in some contexts, but telomerase biology also intersects with cancer biology because many cancers activate telomerase.
- Muscle pathways are systemic. Manipulating myostatin/follistatin signaling may alter muscle mass, but whole-body effects, dose and long-term safety matter.
- Biomarker movement is not automatically rejuvenation. A marker can change without improving hard outcomes such as disability, disease incidence or survival.
- N=1 cannot separate treatment from time, training, diet, measurement noise or regression to the mean.
What would convince me that this worked?
A persuasive demonstration would need pre-registered endpoints, validated assays collected before and after treatment, independent laboratories, transparent adverse-event reporting, and eventually controlled trials. I would want to see not one “age” number but a panel: organ function, strength, metabolic markers, validated aging biomarkers, imaging where relevant, and long-term clinical outcomes.
So is this experiment useless?
No. A self-experiment can be useful for generating hypotheses, discovering unexpected signals, and showing what should be tested next. Its scientific role is closer to an exploratory case report than a treatment recommendation.
The question I still want to follow
The most interesting part is not whether Liz Parrish “reversed aging by X years.” That framing is too crude. The better question is: can a gene therapy safely produce durable, multi-system changes that track with improved healthspan in humans?
That question remains open, and I will continue to treat Parrish’s case as one data point to watch rather than as a verdict.
Sources
Gene therapy for aging: current evidence and future directions, 2026 – review of the emerging field and translational challenges.
Gene therapy targets for aging-associated diseases, 2025 – review of candidate pathways including TERT and other aging-related targets.
Contextualizing aging clocks and biological age, 2024 – explains why different clocks measure different aspects of aging rather than one universal biological age.
Limits of epigenetic clocks as personal biomarkers, 2025 – cautions against interpreting individual clock values as clinical truth.
Medical information
This article may contain published medical evidence, clinical context, personal observations, or hypotheses. These are not equivalent levels of evidence. See the Editorial & Medical Review Policy and Medical Disclaimer. This content is educational and does not provide an individual diagnosis or treatment plan.